


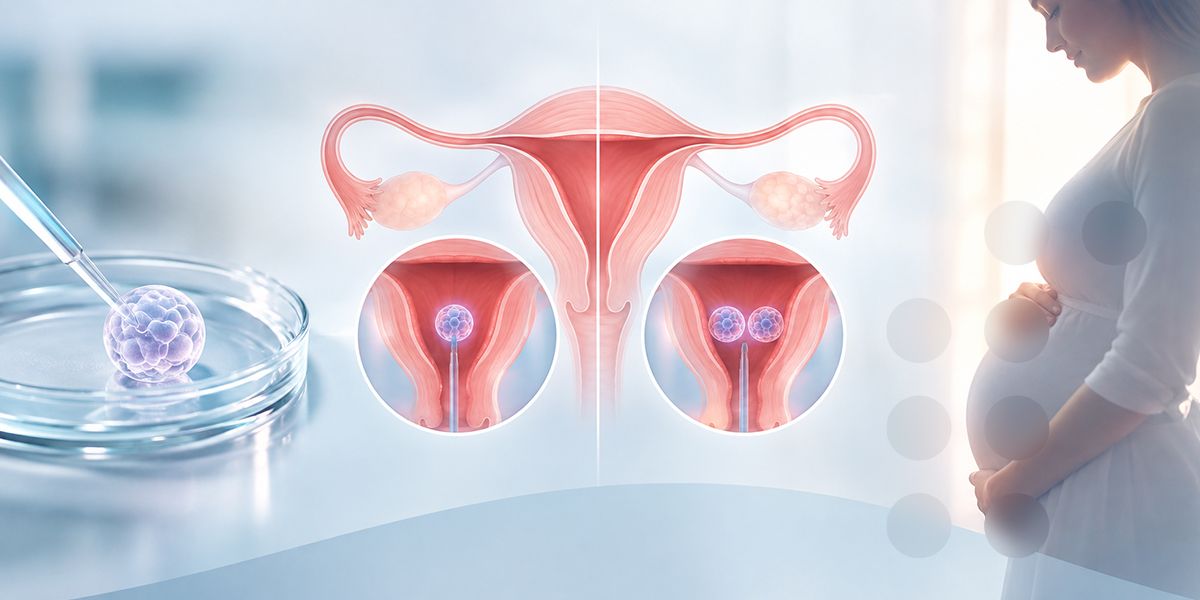

Single vs. Double Embryo Transfer: Balancing IVF Success and Pregnancy Safety
In vitro fertilization (IVF) has advanced significantly through improvements in embryo culture, cryopreservation, embryo selection, and laboratory quality management. However, one important clinical decision remains central to every IVF treatment plan: whether to transfer one embryo or two.
Single embryo transfer (SET) and double embryo transfer (DET) have different implications for implantation, live birth, multiple pregnancy, and maternal and neonatal health. Although transferring two embryos may increase the probability of pregnancy in an individual treatment cycle in some circumstances, it also increases the likelihood of twins and the complications associated with multiple gestation.
Current international guidance increasingly emphasizes elective single embryo transfer (eSET) as the preferred strategy for many IVF patients, particularly when a good-quality embryo is available. The objective is not simply to achieve a positive pregnancy test, but to maximize the likelihood of a healthy live birth while minimizing preventable risks.
This article examines the differences between single and double embryo transfer, the evidence behind each approach, and the practical factors that fertility teams should consider when planning treatment.
-
What Is Single and Double Embryo Transfer?
Embryo transfer is the stage of IVF in which one or more embryos are placed into the uterus using a transfer catheter.
Single embryo transfer (SET) involves transferring one embryo during a treatment cycle. When a patient has multiple suitable embryos and chooses to transfer only one, the procedure is generally referred to as elective single embryo transfer (eSET). Remaining suitable embryos may be cryopreserved for future use.
Double embryo transfer (DET) involves transferring two embryos during the same treatment cycle. If both embryos implant and develop, the pregnancy may result in twins. Occasionally, an embryo may divide after implantation, meaning that transferring one embryo does not completely eliminate the possibility of a multiple pregnancy.
The distinction between SET and eSET is important. SET describes the number of embryos transferred, whereas eSET generally refers to a planned decision to transfer one embryo when other suitable embryos are available.
-
Single vs. Double Embryo Transfer: Key Differences
|
Clinical consideration |
Single embryo transfer |
Double embryo transfer |
|
Number of embryos transferred |
One |
Two |
|
Chance of pregnancy per transfer |
Depends on embryo competence and patient characteristics |
May be higher in some circumstances, but not consistently |
|
Risk of twins |
Low, but not zero |
Substantially higher |
|
Risk of triplets or higher-order pregnancy |
Possible in rare cases involving embryo splitting or other circumstances |
Possible if both embryos implant and one divides |
|
Maternal and neonatal risks |
Avoids most transfer-related risks associated with twins |
Higher risk of complications associated with multiple gestation |
|
Use of additional embryos |
Suitable embryos may be frozen for subsequent transfers |
Two embryos are used in the same transfer |
|
Cumulative treatment potential |
Can allow sequential transfers of available embryos |
May use two embryos in one attempt, potentially reducing the number remaining |
|
Clinical objective |
Prioritizes a healthy singleton birth |
Requires careful consideration of pregnancy probability and multiple-pregnancy risk |
These comparisons are general. Actual outcomes depend on embryo characteristics, maternal health, treatment protocol, laboratory performance, and the definition of success used by the clinic.
-
IVF Success Rates: Per-Transfer Success vs. Cumulative Live Birth
One of the most important distinctions in evaluating embryo transfer strategies is the difference between success per transfer and cumulative live birth.
Success per transfer refers to the outcome of an individual embryo transfer. Depending on the study, it may mean a positive pregnancy test, a clinical pregnancy confirmed by ultrasound, an ongoing pregnancy, or a live birth.
Cumulative live birth rate refers to the probability of achieving at least one live birth after a defined series of treatment attempts, often including subsequent frozen embryo transfers from the same oocyte retrieval.
These outcomes should not be treated as interchangeable.
Transferring two embryos may increase the probability that at least one embryo implants in a particular cycle for some patients. However, this does not automatically mean that DET produces a higher cumulative live birth rate than transferring one embryo at a time.
When suitable embryos are available for cryopreservation, sequential single embryo transfers can provide additional opportunities for pregnancy without deliberately increasing the chance of twins in the first transfer.
The 2024 European Society of Human Reproduction and Embryology (ESHRE) guideline supports eSET as the preferred approach to reducing multiple pregnancies. Its evidence review found no clinical or embryological factor, considered in isolation, that justified routinely recommending DET instead of eSET.
For a meaningful comparison, fertility clinics should report live birth per transfer, cumulative live birth per initiated treatment or oocyte retrieval, and multiple pregnancy rates. These outcomes provide a more complete picture than pregnancy rates alone.
-
Why Is Single Embryo Transfer Increasingly Preferred?
The primary reason for favoring eSET is the reduction of avoidable multiple-pregnancy risk.
A singleton pregnancy is generally associated with lower maternal and neonatal morbidity than a twin pregnancy. Although many twin pregnancies result in healthy babies, they carry a higher probability of complications that may affect both the pregnant patient and the infants.
Maternal risks associated with twin pregnancy
Compared with singleton pregnancies, twin pregnancies are associated with increased risks of:
- Hypertensive disorders of pregnancy, including preeclampsia.
- Gestational diabetes.
- Maternal anemia and greater physiological demands.
- Antepartum and postpartum hemorrhage.
- Cesarean delivery and other delivery-related complications.
- Hospital admission and additional antenatal monitoring.
The magnitude of risk varies according to maternal age, pre-existing conditions, pregnancy characteristics, and the healthcare setting.
Fetal and neonatal risks
The major concern is preterm birth. Twins are substantially more likely than singletons to be born prematurely, which can increase the risk of respiratory problems, feeding difficulties, neonatal intensive care admission, and longer-term developmental complications.
Low birth weight and fetal growth restriction are also more common in multiple pregnancies. When twins share a placenta, additional complications, including twin-to-twin transfusion syndrome, may occur.
The American College of Obstetricians and Gynecologists (ACOG) identifies multifetal gestation and its associated prematurity as major contributors to adverse perinatal outcomes following assisted reproductive technology.
Consequently, minimizing multiple pregnancy is an important component of IVF safety rather than simply a secondary consideration.
-
How Should Clinicians Decide Between SET and DET?
The decision should be individualized, evidence-based, and consistent with applicable national regulations and professional guidelines. The following factors are relevant to clinical assessment.
5.1. Maternal age
Age influences embryo aneuploidy rates, implantation potential, miscarriage risk, and the probability of live birth.
However, maternal age should not be used as an automatic reason to transfer two embryos. The 2024 ESHRE guideline recommends eSET for women both younger than 38 and those aged 38 or older. This recommendation reflects the guideline's assessment of the available evidence and the risks of multiple gestation.
The American Society for Reproductive Medicine (ASRM) provides age- and prognosis-specific guidance on the maximum number of embryos that may be transferred. Its 2021 committee opinion strongly encourages SET in patients younger than 35 with a favorable prognosis and recommends strong consideration of SET for those aged 35–37.
These recommendations are not identical in their approach. Clinicians should apply the relevant guideline, local law, and the patient's complete clinical profile rather than relying on an age threshold alone.
5.2. Embryo developmental stage and quality
Embryos may be transferred at the cleavage stage, typically around day 2 or 3, or at the blastocyst stage, typically around day 5 or 6.
Blastocyst development and morphology can help embryologists rank embryos according to their observed characteristics. However, morphology does not guarantee implantation or live birth, and an embryo with a favorable appearance may still have chromosomal abnormalities.
According to ESHRE, embryo morphology or developmental stage alone should not be used as a reason to recommend DET over eSET.
A practical approach is to select the most suitable embryo using the laboratory's validated assessment system and the patient's clinical information, while considering whether additional embryos can be cryopreserved.
5.3. Embryo chromosomal status
Preimplantation genetic testing for aneuploidy (PGT-A) can provide information about the chromosomal status of a biopsied embryo. When a suitable euploid embryo is available, transferring one embryo is generally the relevant strategy for minimizing multiple gestation.
ASRM recommends limiting the transfer of a euploid embryo to one, regardless of maternal age.
PGT-A has limitations and does not guarantee implantation, an ongoing pregnancy, or a healthy birth. Its clinical value depends on the indication, patient characteristics, testing methods, and the overall treatment plan. It should not be presented as a requirement for every IVF cycle.
5.4. Previous unsuccessful IVF cycles
Repeated unsuccessful transfers can be emotionally and financially difficult. Patients may understandably ask whether transferring two embryos would improve their next attempt.
However, the number of previous unsuccessful ART treatments should not, by itself, determine whether DET is used. ESHRE specifically advises against basing this decision solely on the number of failed treatments.
A more useful response is to review the previous cycle records, embryo development, transfer conditions, uterine and endometrial assessment, and other relevant clinical findings. Any further investigations should be selected according to the patient's history and established indications.
5.5. Maternal medical conditions
Pre-existing conditions can make a multiple pregnancy particularly hazardous. These may include significant cardiovascular disease, poorly controlled hypertension, or other conditions in which the additional physiological demands of twin pregnancy could increase maternal risk.
In such circumstances, the clinical team should prioritize pregnancy safety. ASRM advises that patients with medical conditions that could cause significant morbidity in a multiple pregnancy should not have more than one embryo transferred.
5.6. Donor-oocyte cycles and gestational carriers
Donor-oocyte treatment requires particular attention to embryo-transfer strategy. The age of the oocyte donor is relevant to embryo prognosis, but it does not remove the risks of a multiple pregnancy.
For gestational-carrier cycles, the health of the person carrying the pregnancy must be central to the decision. ASRM strongly recommends single embryo transfer in these cycles, and ESHRE advises avoiding DET in treatment involving donor oocytes, donated embryos, or gestational carriers because of the associated pregnancy risks.
-
A Practical Decision-Making Framework for IVF Clinics
The following workflow can help fertility teams structure counseling and document the rationale for their transfer strategy.
Step 1: Review the patient's clinical profile. Assess maternal age, medical history, reproductive history, previous treatment outcomes, and factors relevant to pregnancy safety.
Step 2: Review the available embryos. Consider developmental stage, morphological assessment, genetic testing results when available and indicated, cryopreservation suitability, and the clinic's validated embryo-selection procedures.
Step 3: Establish the treatment objective. Discuss the probability of live birth, the risk of multiple gestation, and the distinction between success per transfer and cumulative live birth.
Step 4: Consider sequential transfers. When suitable embryos can be cryopreserved, explain the option of transferring one embryo now and using another in a subsequent cycle if needed.
Step 5: Apply the relevant guideline and regulations. Consult current professional guidance, national requirements, and the clinic's approved protocols. Avoid treating age, embryo morphology, or previous failures as a sufficient reason for DET in isolation.
Step 6: Document shared decision-making. Record the recommended approach, the clinical rationale, the patient's questions and preferences, the discussion of multiple-pregnancy risks, and informed consent.
Step 7: Audit clinical outcomes. Review live birth per transfer, cumulative live birth, multiple pregnancy, prematurity, and relevant neonatal outcomes. Stratifying results by age, embryo stage, and treatment type helps ensure that comparisons are clinically meaningful.
This framework supports consistent counseling without replacing individualized clinical judgment.
-
Counseling Patients: Questions That Should Be Addressed Before Transfer
Before consenting to embryo transfer, patients should understand the following:
- What is my estimated probability of live birth with one embryo?
- How does the clinic estimate the cumulative chance of live birth if a second embryo is frozen and transferred later?
- What is the estimated risk of twins if two embryos are transferred?
- Are there maternal health factors that make a multiple pregnancy more hazardous for me?
- What information is available about the embryos, and what are the limitations of that information?
- What would happen to any suitable embryos not transferred in this cycle?
- What additional costs, delays, or treatment steps could be associated with a later frozen embryo transfer?
- Which professional guidelines and local regulations apply to my treatment?
Patients should receive individualized estimates where reliable data are available. Clinic-wide averages may not accurately represent an individual's prognosis, and pregnancy rates should not be presented as guaranteed outcomes.
Financial and access considerations also matter. If the cost of another transfer creates pressure to transfer two embryos at once, clinics should explain the medical trade-offs and discuss available financing, insurance, or treatment options where applicable.
-
Common Misconceptions About Embryo Transfer
Myth 1: Transferring two embryos doubles the chance of success.
Not necessarily. Implantation probabilities are not simply additive, and the outcomes depend on embryo competence and patient characteristics. A higher chance of pregnancy in one transfer does not automatically translate into a higher cumulative live birth rate.
Myth 2: Twins are simply two successful outcomes instead of one.
A twin pregnancy is a distinct clinical situation with higher risks of prematurity and maternal complications. The number of babies is not an adequate measure of treatment quality without considering their health and the safety of the pregnancy.
Myth 3: Older patients should always receive two embryos.
Age is relevant, but it should not be used in isolation. ESHRE recommends eSET across age groups, while ASRM provides more individualized limits based on age, embryo characteristics, and prognosis. The applicable guideline and clinical circumstances should guide the decision.
Myth 4: A good-quality embryo guarantees a healthy baby.
Morphological assessment helps with embryo selection but cannot guarantee implantation, normal development, or live birth. Even a euploid embryo may fail to implant or may not result in a live birth.
Myth 5: One embryo eliminates the possibility of twins.
A single embryo can occasionally divide and result in monozygotic twins. SET substantially reduces transfer-related multiple-pregnancy risk but does not reduce it to zero.
-
The Role of Medical Device Quality in Assisted Reproduction
The embryo-transfer decision is only one component of a successful IVF program. Reliable outcomes also depend on the broader treatment pathway, including laboratory conditions, embryo handling, traceability, validated procedures, and the consistent performance of medical devices used during assisted reproduction.
Embryo-transfer catheters and other devices used in reproductive medicine should be selected and handled according to their intended purpose, manufacturer instructions, applicable regulatory requirements, and the clinic's validated procedures.
For fertility centers, a structured approach to device selection and quality management helps support procedural consistency and patient safety. Device performance should be assessed within the complete clinical workflow rather than as an isolated determinant of IVF success.
For manufacturers such as rada, continued attention to product quality, healthcare-provider feedback, and the practical needs of fertility laboratories forms part of the broader effort to support reproductive healthcare professionals.
-
Conclusion: Balancing IVF Success With Pregnancy Safety
The choice between single and double embryo transfer should be based on the goal of achieving a healthy live birth, not solely on maximizing the probability of pregnancy in an individual treatment cycle.
Double embryo transfer may increase the chance of pregnancy in some circumstances, but it also increases the risk of twins and their associated maternal, fetal, and neonatal complications. Single embryo transfer reduces this avoidable risk and, when suitable embryos are available for cryopreservation, allows patients to pursue additional treatment opportunities through sequential transfers.
The 2024 ESHRE guideline and the ASRM/SART guidance emphasize reducing multiple gestation while maintaining effective IVF treatment. Their recommendations differ in some details, making it important for clinicians to follow applicable local regulations and consider the full clinical context.
For fertility specialists, the practical priority is clear: evaluate the patient and embryos carefully, explain both immediate and cumulative outcomes, document shared decision-making, and monitor results beyond pregnancy rates alone. A successful IVF program should measure not only whether pregnancy occurs, but also whether it leads to a healthy birth with the lowest reasonably achievable risk.
Medical disclaimer: This article is intended for educational purposes and does not replace individualized advice from a qualified fertility specialist. Embryo-transfer decisions should follow current clinical guidance, applicable regulations, and the patient's individual medical circumstances.
References
- European Society of Human Reproduction and Embryology (ESHRE). ESHRE Guideline: Number of Embryos to Transfer During IVF/ICSI. Human Reproduction. 2024;39(4):647–657
- Practice Committee of the American Society for Reproductive Medicine (ASRM) and Practice Committee of the Society for Assisted Reproductive Technology (SART). Guidance on the Limits to the Number of Embryos to Transfer: A Committee Opinion. Fertility and Sterility. 2021;116(3):651–654
- American College of Obstetricians and Gynecologists (ACOG). Perinatal Risks Associated With Assisted Reproductive Technology. Committee Opinion.
- Human Fertilisation and Embryology Authority (HFEA). Risks of Fertility Treatment.
- Human Fertilisation and Embryology Authority (HFEA). Decisions to Make About Your Embryos.
- American College of Obstetricians and Gynecologists (ACOG). Multiple Pregnancy. Patient FAQ.